
What moved, and who pays.
CMS finalized the CY2027 OPPS/ASC rule (CMS-1850-F) and Physician Fee Schedule (CMS-1848-F) on November 4. The 340B cut came in softer than proposed. The physician conversion factor came in harder. And a narrowed same-day E/M reduction now lands on every specialty that bills 0-day procedures. This briefing gives each specialty we serve the need-to-know, and compares the final rules with what we told clients in August.

Tell us who you are and your download starts right away.
If the download did not start, use the button below. The link works for 30 minutes. Questions on your 2027 exposure: sales@fulcrumhp.com.
Download the Briefing See how we turn rules into decisions →Sources: CMS, CY 2027 Medicare Physician Fee Schedule Final Rule (CMS-1848-F) fact sheet and CY 2027 OPPS and ASC Final Rule (CMS-1850-F) fact sheet, both November 4, 2026. Proposed values from the July 2026 proposed-rule fact sheets. National figures before geographic adjustment.
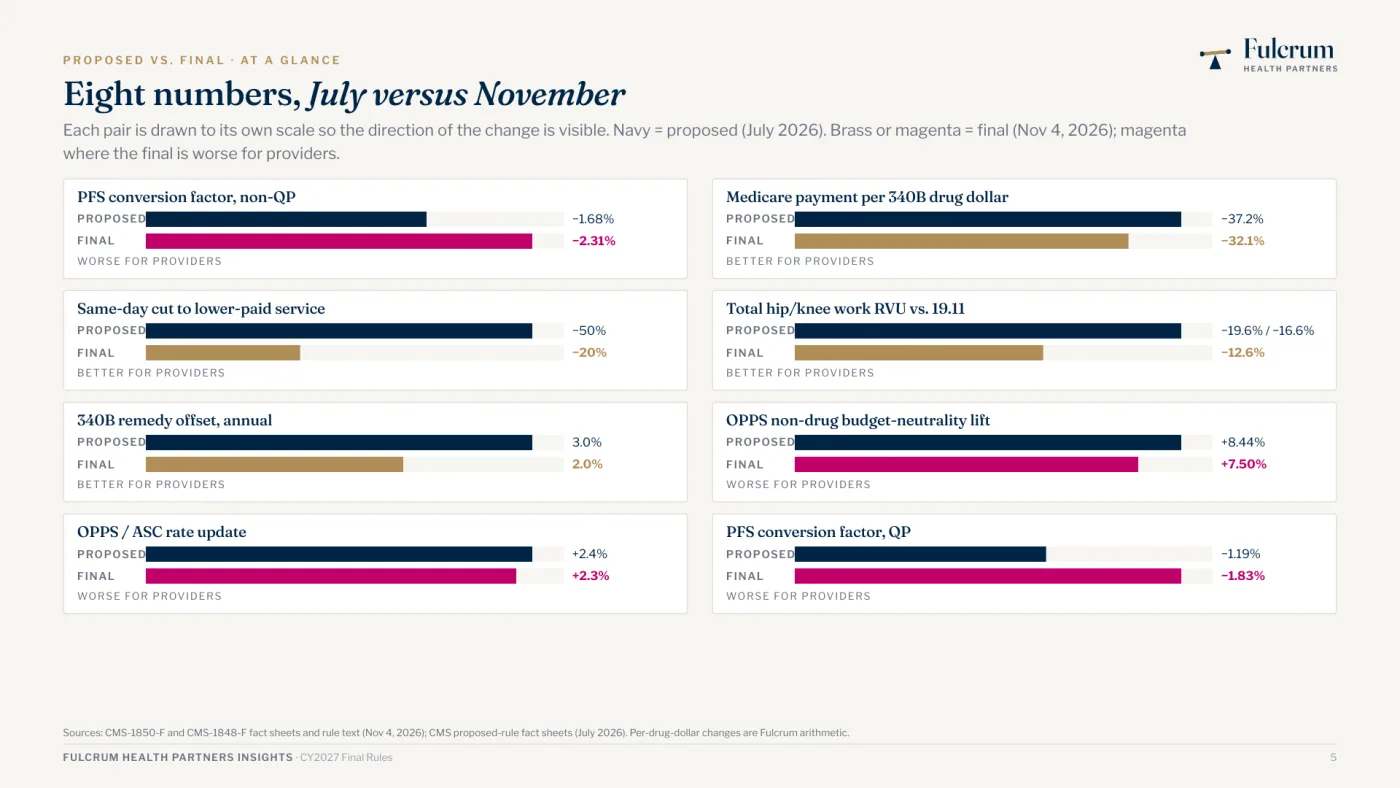
Our August CFO briefing modeled the proposed rules. The final rules moved in the direction we argued on 340B, and against providers on the physician conversion factor. The briefing tracks every headline figure; the seven that matter most are below.
| Provision | Proposed (Jul 2026) | Final (Nov 4, 2026) | For providers |
|---|---|---|---|
| 340B drug payment | ASP − 33.4% | ASP − 28% | Better |
| 340B remedy offset | 0.5% → 3%; done about CY2029 | 0.5% → 2%; done CY2031 | Better |
| OPPS / ASC update | +2.4% | +2.3% | Worse |
| PFS conversion factor | Non-QP $32.84 (−1.68%) QP $33.17 (−1.19%) | Non-QP $32.63 (−2.31%) QP $32.95 (−1.83%) | Worse |
| Same-day E/M + global procedure | Lower service at 50%; 0-, 10- and 90-day globals | Lower service at 80%; 0-day only; same specialty in group | Better |
| Total hip / knee work RVU (27130, 27447) | 15.37 / 15.94, from 19.11 | 16.70 each (−12.6%) | Better |
| Inpatient-only list / ASC list | −637 IPO / +618 ASC | Finalized as proposed | Mixed |
Sources: CMS-1850-F and CMS-1848-F fact sheets (Nov 4, 2026) for the drug rate, offset, updates, conversion factors, same-day policy and the 637 inpatient-only removals. Hip and knee work RVUs and the 618 ASC additions are from the rule text as reported by Medical Economics and AHA News (Nov 4, 2026). Proposed values from the July 2026 proposed rules.
Every figure in the briefing is traditional Medicare. It reaches MA and commercial revenue only through contract language, and most of that language was written before anyone modeled a 2.31% conversion factor cut or a 32% 340B reduction.
Each sector page in the briefing carries what CMS finalized, what it means, and a strategic implication for the contract table. The one-line verdicts:
Plus 21 physician specialty briefs: Allergy & Immunology, Cardiology, Endocrinology, ENT, Infectious Disease, Nephrology, Neurology, Neurosurgery, OB/GYN, Ophthalmology, Pediatrics, Physical Medicine & Rehab, Podiatry, Pulmonology, Rheumatology, Sleep Medicine, General Surgery, Urology, Vein Centers, Hospital-Based Providers, and Ancillary Providers & Labs.
Agreements written as a percent of the current Medicare fee schedule, drug terms pegged to the Medicare payment amount, and MA contracts paying "Original Medicare equivalent" import these changes on January 1. Fixed-year schedules, proprietary fee schedules and case rates do not. The briefing closes with five steps before January claims adjudicate:
Fulcrum Health Partners turns rules like these into code-level financial impact, service-line and site-of-care strategy, and decisions boards and investors can act on. We model the rule across Medicare, MA and commercial books, assess contract portfolio exposure, and align the 2027 budget to it.
Educational summary of traditional Medicare policy. Not legal, actuarial or reimbursement advice; review contract-specific questions with counsel.